


Introduction
Retroperitoneal fibrosis (RPF) is a rare chronic disorder characterized by formation of a fibroinflammatory mass in the retroperitoneal space. The most common type of RPF is idiopathic, while the remaining cases, referred to as secondary RPF, are associated with malignancies, infections, radiotherapy, drugs and prior surgery [1–5]. Idiopathic retroperitoneal fibrosis (IRF), along with inflammatory abdominal aortic aneurysms and perianeurysmal fibrosis, is part of a broader spectrum of disorders known as chronic periaortitis (CP) [1]. The fibrous tissue typically forms around the abdominal aorta and iliac arteries but can also affect other retroperitoneal structures, such as ureters, kidneys and inferior vena cava, which can lead to severe complications including ureteral obstruction (observed in 60–70% of cases), hydronephrosis, impaired kidney function and deep vein thrombosis [2, 3]. The most frequent clinical signs of RPF involve abdominal and/or lower back pain, though other less commonly observed symptoms include weight loss, fatigue, nausea, anorexia, and others [3, 4]. Retroperitoneal fibrosis may also be a manifestation of immunoglobulin G4-related disease (IgG4-RD), which may affect other organs, most commonly the pancreas, bile ducts, and lacrimal and salivary glands. In cases of IgG4-RD, histopathological examination is necessary to confirm the diagnosis [6]. According to the literature, 30–60% of RPF cases are caused by IgG4-RD. No significant differences in treatment efficacy have been observed between patients with IRF and those with IgG4-RD; however, elevated serum IgG4 concentrations may be associated with a less favorable therapeutic response and an increased risk of relapse [7, 8]. The RPF diagnosis is based on clinical evaluation, laboratory tests, imaging and, if needed, a biopsy. It is crucial to exclude malignancies, infections, and other secondary causes of RPF [1, 5]. Laboratory studies frequently reveal increased acute-phase reactants (APR), anemia, and an elevated creatinine serum level secondary to ureteral compression. Increased concentration of C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) are present in approximately 80% of patients and are used to monitor disease activity [1, 3, 4]. Contrast-enhanced computed tomography (CT) is considered as the gold standard in both diagnosis and treatment monitoring, as it provides detailed imaging of the periaortic soft tissue mass and the involvement of other retroperitoneal structures [2, 5]. Gadolinium magnetic resonance imaging (MRI) is an alternative in cases in which CT is contraindicated. Although it illustrates a more detailed contrast between soft tissues, and diffusion-weighted imaging can be helpful to distinguish chronic RPF from neoplasms, it does not differentiate between active and chronic RPF [9]. 18F-fluorodeoxyglucose positron emission tomography (FDG-PET) is useful to assess the metabolic activity of retroperitoneal masses at the introduction of treatment and during follow-up [2, 5]. Biopsy is considered an effective method for confirming diagnosis in cases of atypical radiological presentation of RPF or when malignancy is suspected. In the absence of diagnostic uncertainty, biopsy can be omitted, particularly considering the invasive nature of the procedure [5, 10–13].
The treatment options include pharmacotherapy and urological management. The most common and highly effective drugs used to treat IRF are glucocorticosteroids (GCs), although there is a high risk of recurrence of the disease after treatment discontinuation [10–12]. Use of other immunosuppressive agents as disease-modifying therapy is increasingly common and reduces the dose and duration of treatment with GCs [14–21]. When ureteral obstruction with impaired kidney function occurs, urological procedures may be necessary. Ureteral stenting is the most frequently performed procedure, with nephrostomy being another conservative option. Ultimately, severe and refractory cases may require ureterolysis [5].
Since there are no recommendations for treating IRF, a summary of available pharmacological therapeutic choices is necessary.
Material and methods
A search of medical databases including PubMed and Scopus was performed for articles published between January 2000 and February 2025 using the following keywords: retroperitoneal fibrosis, idiopathic, immunosuppressive, treatment, GC, tamoxifen (TMX), mycophenolate mofetil (MMF), azathioprine (AZA), methotrexate (MTX), cyclophosphamide (CYC), and rituximab (RTX). The initial search was conducted in October 2024 and the final one in March 2025.
The inclusion criteria were studies written and published in English focusing on the treatment of IRF (more than 50% of patients with IRF), discussing treatment of at least 6 patients using no more than 2 different medications, excluding GCs. Due to the rarity of the disease, most studies included small patient cohorts. Therefore, only studies involving more than 6 patients and using no more than 2 additional drugs besides GCs were included in the analysis. This approach allowed for a comparison of treatment efficacy beyond individual case reports, thereby increasing the credibility of treatment effectiveness.
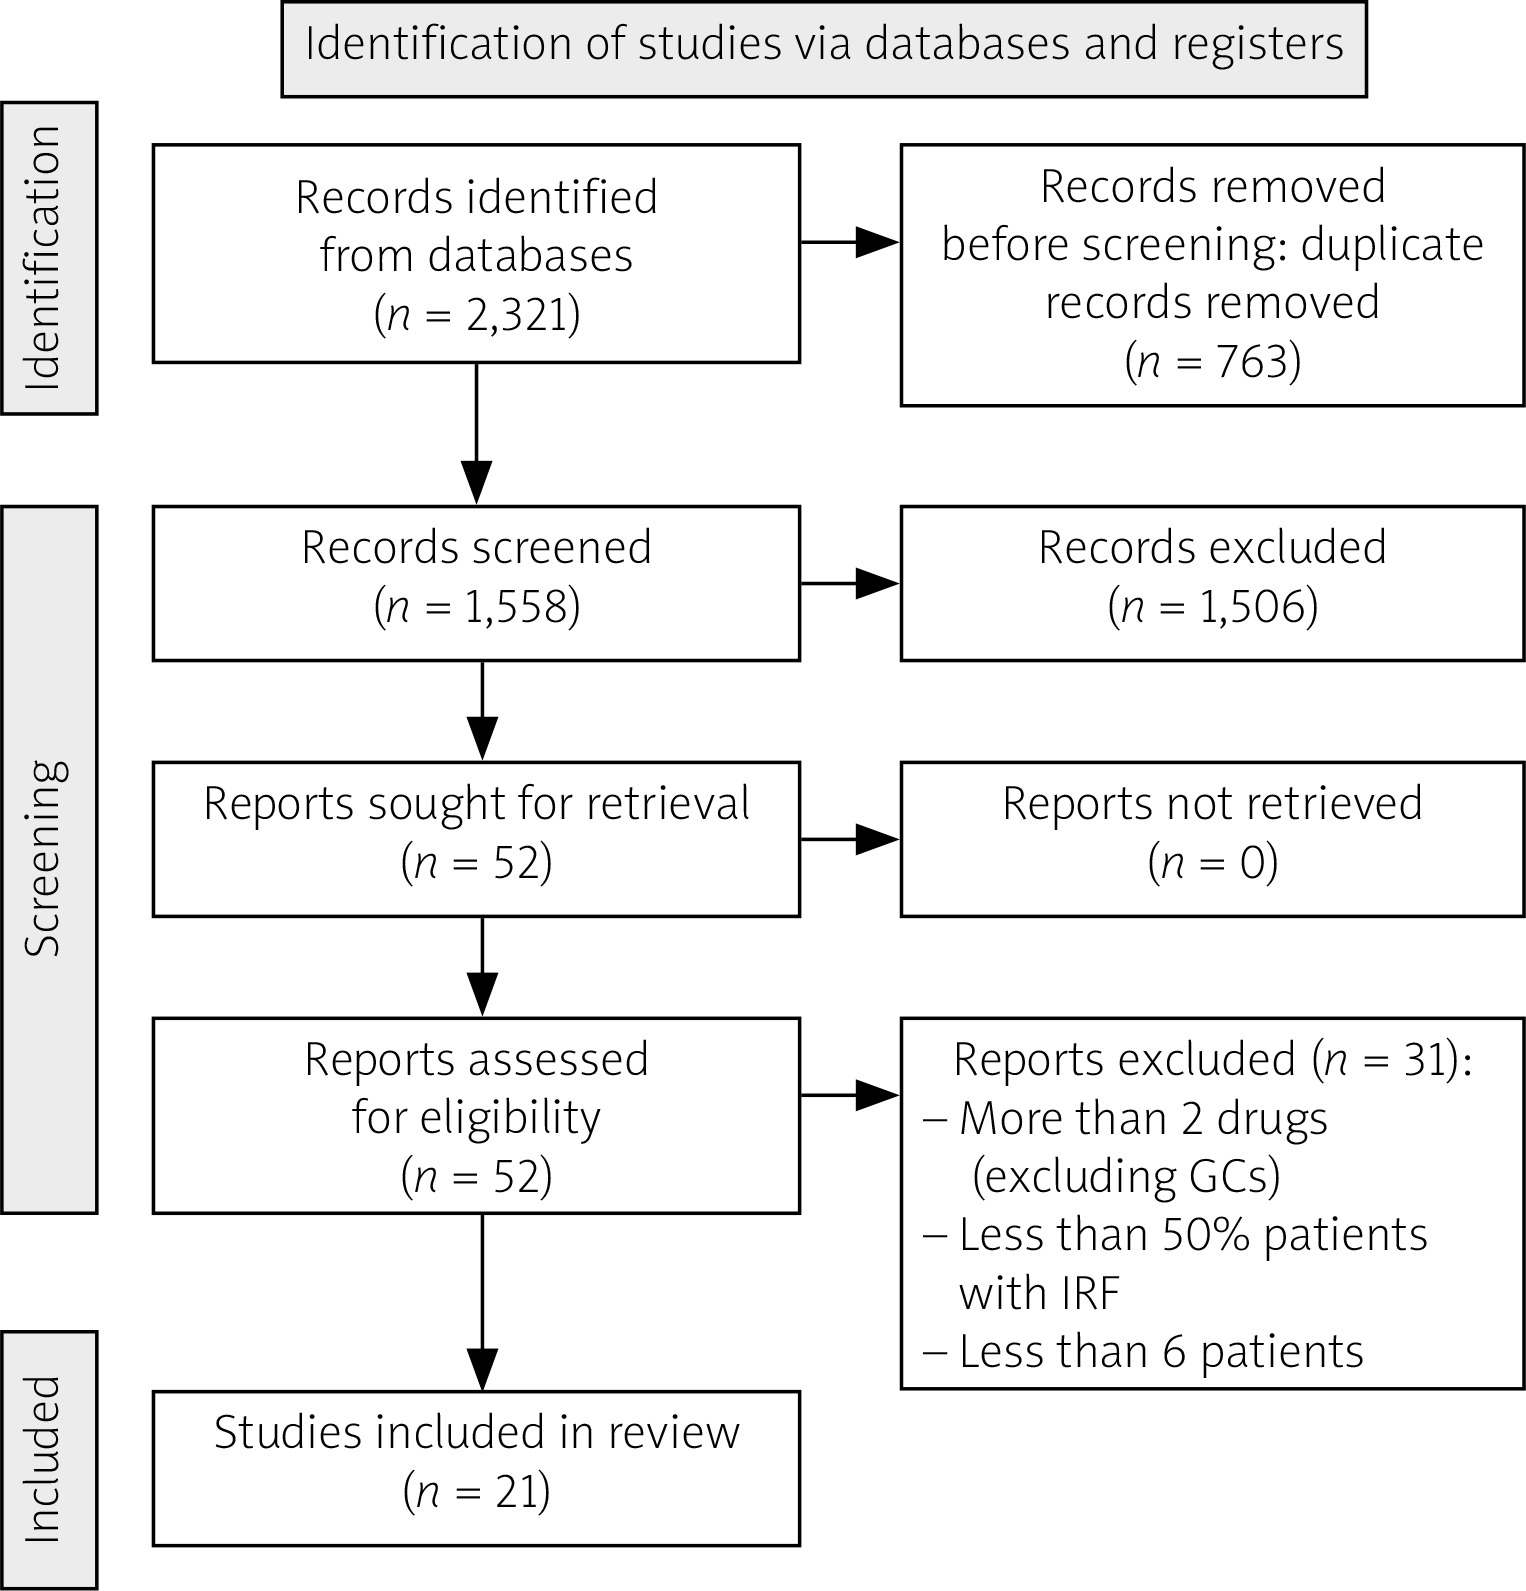
Articles describing treatment of more than 50% of patients with IgG4-related RPF or CP were not included. The PRISMA plot is presented in Figure 1. Twenty-one studies met the criteria for this narrative review.
Figure 1
PRISMA flow diagram illustrating literature search and study selection.
IRF – idiopathic retroperitoneal fibrosis, GCs – glucocorticosteroids.
Importantly, most of the authors define successful treatment and recurrence of the disease differently. Outcomes such as a reduction in clinical symptoms and periaortic fibrous mass, as well as a decrease of inflammatory marker levels and removal of ureteral stents or nephrostomy in various combinations, were perceived as a satisfactory response to therapy. This is presented in the tables below. Table I summarizes studies on the treatment of IRF with GCs and TMX. Table II provides a summary of studies on immunosuppressive therapy, used in combination with GCs, while Table III presents the treatment of IRF with biological agents, in some cases combined with GCs.
Table I
Studies evaluating glucocorticoids and tamoxifen for idiopathic retroperitoneal fibrosis
| Author | Type of study | n | Treatment | Initial dose of GCs | Stents* | Mass regression | Treatment success** | Relapse |
|---|---|---|---|---|---|---|---|---|
| Fry et al. 2008 [10] | Retro | 24 | Prednisolone | 30 mg | 18/20 patients | ND | C+A | 6/24 |
| Van Bommel et al. 2007 [11] | Retro | 24 | Prednisone | 60 mg | 3/5 patients | 19/24 | 18/24 C+A+M+U | 13/18 |
| Morin et al. 2019 [12] | Retro | 23 | Prednisone | 1 mg/kg | ND | ND | 21/23 C+A+M/S | 6/23 |
| Azizi et al. 2020 [13] | Retro | 12 | Steroids | 0.5–1 mg/kg | ND | ND | 9/12 C+A+M/S | 0/12 |
| Van Bommel et al. 2012 [24] | Pros | 55 | TMX 40 mg | None | ND | 47/55 | 36/55 C+M+U | ND |
| Brandt et al. 2014 [25] | Retro | 31 | TMX 40 mg | None | 17/29 patients | 22/31 | ND | 0/31 |
| Vaglio et al. 2011 [26] | RCT | 18 | Prednisone | 0.5 mg/kg | ND | ND | ND | 3/18 |
| Vaglio et al. 2011 [26] | RCT | 18 | TMX 0.5 mg/kg | None | ND | ND | ND | 9/18 |
| Van der Bilt et al. 2016 [27] | Retro | 50 | Prednisone | 60 mg/kg | ND | 42/50 | 31/44 C+M+U | 21/31 |
| Van der Bilt et al. 2016 [27] | Retro | 68 | TMX 0.49 mg/kg | None | ND | 43/68 | 28/48 C+M+U | 6/28 |
| Brandt et al. 2013 [28] | Retro | 12 | Prednisone | 1 mg/kg | 11/18 stents | 10/12 | ND | 2/12 |
| Brandt et al. 2013 [28] | Retro | 12 | TMX 40 mg | None | 10/16 stents | 12/12 | ND | 0/12 |
Table II
Studies evaluating non-biologic immunosuppressive agents for idiopathic retroperitoneal fibrosis
| Authors | Type of study | n | Drug other than GCs | Initial dose of GCs | Stents* | Massregression | Treatment success** | Relapse |
|---|---|---|---|---|---|---|---|---|
| Scheel et al. 2007 [14] | Pros | 7 | MMF 2 g | Prednisone 40 mg | 10/11 stents | 6/7 | ND | 0/7 |
| Adler et al. 2008 [15] | Retro | 9 | MMF 2 g | 1 mg/kg | 5/7 patients | 9/9 | 9/9 | 0/9 |
| Scheel et al. 2011 [16] | Pros | 28 | MMF 2 g | Prednisone 40 mg | 25/29 stents | 25/28 | ND | 2/28 |
| Obrenčević et al. 2019 [17] | Retro | 13 | MMF 2 g | Prednisone 0.5 mg/kg Methylprednisolone | 6/7 patients | 13/13 | 13/13 A+M | 3/13 |
| Marcolongo et al. 2004 [18] | Retro | 15 | AZA 2.5 mg/kg | Prednisone 1–1.5 mg/kg | ND | ND | 15/15 C+A+U | 4/15 |
| Marcolongo et al. 2004 [18] | Retro | 11 | CYC 2 mg/kg or i.v. pulses | Prednisone 1–1.5 mg/kg | ND | ND | 10/11 C+A+U | 3/10 |
| Prucha et al. 2016 [19] | Retro | 26 | AZA 100 mg | Prednisone 0.75–1 mg/kg | 32/36 stents | 26/26 | C+M+U | 2/26 |
| Alberici et al. 2013 [20] | CT | 16 | MTX 15 mg/week | Prednisone 0.5–1 mg/kg | 1/3 patients | Slight reduction | 11/14 C+A+M | 4/11 |
| Vianello et al. 2023 [21] | Retro | 15 | MTX 12.5 mg/week | Prednisone 0.8–1 mg/kg | 6/6 patients | 14/15 | 14/15 C+A+M | 2/14 |
| Gao et al. 2023 [29] | CT | 8 | SRL 2 mg initially | Prednisone 0.8 mg/kg | ND | Nearly by half | ND | ND |
A – acute phase reactant normalization, AZA – azathioprine, C – clinical improvement, CYC – cyclophosphamide, CT – clinical trial, GCs – glucocorticosteroids, M – mass regression, MMF – mycophenolate mofetil, MTX – methotrexate, ND – no data, Pros – prospective, Retro – retrospective, SRL – sirolimus, U – resolution of ureteral obstruction.
Table III
Studies evaluating biologic agents for idiopathic retroperitoneal fibrosis
| Authors | Type of study | n | Biological drug | Initial dose of GCs | Stents* | Mass regression | Treatment success** | Relapse |
|---|---|---|---|---|---|---|---|---|
| Oztas et al. 2023 [30] | Retro | 13 | RTX 1 g i.v. (1–6) | Prednisone 10 mg | 2/8 patients | Significant | ND | ND |
| Boyeva et al. 2020 [31] | Retro | 10 | RTX 1 g i.v. (2) | 3 patients – dose unknown | None | Significant | ND | ND |
| Wang et al. 2023 [32] | Clinical trial | 12 | TCZ 8 mg/kg every 4 weeks | None | 2/4 patients | 12/12 | 10/11 C+A+M | ND |
At the same time, a search for review articles was conducted. Steimer et al. [22] published a meta-analysis on the subject, but the literature search only included studies published up to 2021, and therefore treatment with MTX, tocilizumab (TCZ), and sirolimus (SRL) was not discussed. Carey et al. [23] focused on RPF patients with obstructive uropathy and did not compare medical therapeutic methods directly.
Results
A review of the literature on the pharmacological treatment of IRF is presented below.
Glucocorticosteroids
Fry et al. [10] examined the effect of the mean starting dose of 30 mg of prednisolone in 24 IRF patients, 96% of whom had significant renal impairment at baseline. A maintenance dose of GCs was administered for 2–3 years. Successful therapy enabled stent removal in 18 out of 20 patients. Relapse was diagnosed in 25% of study participants after a mean follow-up of 52 months, defined as worsening of kidney function, ESR, or a periaortic mass enlargement detected in a CT scan. It is worth noting that 1 patient, who was not included in the study at the end, had a histopathological diagnosis of IRF and improved after treatment; however, his imaging findings were concerning, and he eventually developed lymphoma. It is crucial to closely observe RPF patients and if there is even a slight suspicion of malignancy, it should be examined and excluded [10]. Van Bommel et al. [11] described treatment of 24 patients with an initial dose of 60 mg of prednisone daily, gradually reduced and maintained in a small dose for 12 months. 75% of study participants showed clinical improvement, mass regression on imaging, ureteral obstruction resolution and normalization of acute phase reactants, and as a result were considered a treatment success. Up to 72% of responders required reintroduction of pharmacotherapy due to a recurrence of disease symptoms, on average 10 months after the discontinuation of GCs. Morin et al. [12] treated 23 IRF patients with an initial dose of 1 mg/kg/day of prednisone and evaluated the efficacy of GCs alongside the correlation between persistent fluorodeoxyglucose (FDG) uptake in positron emission tomography (PET) and the risk of relapse. Up to 91% of study participants were in remission during follow-up, described as a decrease in APR and creatinine levels, resolution of disease symptoms and reduction or stabilization of retroperitoneal tissue on imaging, even though almost 70% had a high FDG uptake in PET. Altogether, 26% of patients had a relapse classified as recurrence of symptoms, hydronephrosis, or mass enlargement, and all of them were still receiving a maintenance dose of GC. It was reported that high FDG uptake in PET 10 months after treatment introduction was associated with an increased risk of relapse. Azizi et al. [13] achieved remission defined as clinical improvement, decrease in CRP, ESR, and creatinine levels and reduction/stable mass on imaging in 75% of RPF patients using the primary dose of 0.5–1 mg/kg per day of GCs. All of them had hydronephrosis and had been previously treated with ureteral stents or nephrostomy. None of the study participants had a relapse.
Tamoxifen
Van Bommel et al. [24] estimated the efficacy of treatment with twice daily 20 mg TMX for 2 years in 55 patients, both women and men. Therapy was considered effective in 65% of study participants, causing alleviation of symptoms, soft tissue reduction, and resolution of ureteral obstruction. Side effects were usually mild, including hot flashes, fatigue, and loss of libido. Two patients had mood disturbances requiring dose reduction and another 2 had pulmonary embolism. Brandt et al. [25] also examined the efficiency of 40 mg of TMX per day in 31 patients with IRF and reported similar results. After a mean treatment duration of 13.3 months, fibrous mass reduction was reported in 71% of patients, and ureteral stents were removed in 58.6% of patients. Tamoxifen was discontinued in 2 participants due to thromboembolic events and in 1 patient because of painful ovarian cysts.
Studies comparing glucocorticosteroids and tamoxifen
Three studies comparing treatment of IRF with GCs to TMX were found. In the only randomized controlled study survey assessing medical therapy of idiopathic RPF, Vaglio et al. [26] estimated the risk of relapse after treatment with prednisone or TMX. After achieving clinical and laboratory remission with daily prednisone (1 mg/kg) administered for 1 month, 36 patients with IRF were divided into 2 groups. Eighteen of them continued taking prednisone 0.5 mg/kg daily, which was gradually tapered and discontinued after 8 months of treatment. The other half were treated with 0.5 mg/kg of TMX daily for 8 months. After 26-month follow-up, relapse was characterized as presence of disease symptoms in association with an increase in APR, hydronephrosis, or periaortic mass enlargement in CT/MRI. It occurred in 17% of prednisone-treated patients and 50% of patients treated with TMX. Van der Bilt et al. [27] reported that prednisone is more effective in achieving remission; however, the recurrence rate was lower in patients treated with TMX in this study. Fifty patients started their therapy at a median starting dose of 60 mg of prednisone daily, which was tapered slowly until drug withdrawal after 14 months. Sixty-eight patients in the second group were treated with 40 mg/day of TMX monotherapy for 24 months. The results revealed a quicker reduction of disease symptoms and mass regression at the first follow-up CT scan as well as a greater decrease in CRP, ESR, and creatinine serum levels in the prednisone group. The overall treatment outcome was more favorable in patients receiving prednisone monotherapy (70.5%) than in patients treated with TMX (58.3%), although the difference was not statistically significant. Interestingly, recurrence rate, defined as recurrence of disease symptoms or periaortic tissue enlargement, was lower in the TMX group (21.4% vs. 67.7%). Brandt et al. [28] treated 1 group of 12 patients with IRF with prednisone (initial dose 1 mg/kg every other day) for 1 year and the other group of 12 patients with TMX 20 mg twice a day for the same period. There was no significant difference in mass regression or in the amount of removed stents after treatment in the 2 groups.
Mycophenolate mofetil
Scheel et al. [14] proved the therapeutic value of MMF in a prospective study. Seven patients with IRF were treated with a combined regimen of 40 mg of prednisone daily, tapered and discontinued after 6 months, and 1,000 mg of MMF twice daily. This management allowed the removal of 10 out of 11 stents and decreased the periaortic fibrous mass in 6 patients [14]. In a study by Adler et al. [15], 9 patients received 1,000 mg of MMF twice a day and prednisone at the initial dose of 1 mg/kg/day. All of the participants had periaortic infiltrate reduction and 5 out of 7 had their ureteric stents removed. None of the patients had a relapse. Promising results were also obtained by Scheel et al. [16] in a prospective study on 28 patients with RPF treated with 40 mg/day of prednisone and 1,000 mg of MMF twice daily. Mass regression was observed in 89% of the study participants, and 25 out of 29 stents were removed. Only 7% of patients had a recurrence of the disease. It was the only study which reviewed the side effects of this combined therapy. Two patients developed shingles, and 1 experienced worsened diabetes control.
Obrenčević et al. [17] treated 13 patients with MMF at an initial dose of 1,000 mg twice a day for 6 months. Eight out of all participants were additionally treated with a starting dose of 0.5 mg/kg/day of prednisone, and the rest of the patients received 250 mg of methylprednisolone for 3 days followed by 0.5 mg/kg of oral prednisone apart from MMF. Fibrous mass reduction was observed in all of the participants, while stents were removed in 6 out of 7 patients. Relapse was defined as enlargement of periaortic mass and increase of acute phase reactant levels. The authors reported a 23% recurrence rate, which was significantly higher compared to the other studies investigating therapy with MMF. However, it might be attributable to a long median follow-up of 99.4 months.
Azathioprine and cyclophosphamide
Marcolongo et al. [18] reported results supporting the effectiveness of AZA and CYC in treating IRF patients with ureteral obstruction. All patients received 1–1.5 mg/kg/day of prednisone for 3 weeks, then the dose was gradually reduced to a complete withdrawal after 6 months. Fifteen participants were also prescribed AZA 2.5 mg/kg/day for 6 months, which was then tapered to 1.5 mg/kg/day for the subsequent 6 months, and 11 patients were treated with oral or intravenous CYC for 6 months. All study participants showed resolution of ureteral obstruction and clinical improvement, except 1 patient treated with CYC, who died of pneumonia. Seven of all the patients relapsed and required other therapy. Prucha et al. [19] presented an analysis of the treatment of 26 IRF patients with prednisone (starting dose of 0.75–1 mg/kg/day) and 100 mg of AZA daily for 6 months. All of the study participants had retroperitoneal mass reduction and the treatment allowed the removal of 89% of stents. Two patients experienced a relapse.
Methotrexate
Two studies on treating IRF with MTX were found, and in both cases the drug was used in relapsing patients. Remission was defined as clinical improvement, decrease of APR levels, and periaortic mass reduction. Importantly, both of the authors administered low doses of MTX. Alberici et al. [20] started the treatment with prednisone 0.5–1 mg/kg daily, reduced to the maintenance dose of 2.5–5 mg/day by 6 months along with MTX 15–20 mg per week in 16 relapsing patients. In 79% of study participants, the treatment was successful; 36% of these patients relapsed after MTX discontinuation. The rest of the patients continued the treatment and remained in remission. Due to sepsis and liver toxicity in 1 patient, the medications were withdrawn. Vianello et al. [21] reported high effectiveness of treatment with MTX in 15 relapsing or GC-refractory patients with IRF. The patients were prescribed MTX in a median dose of 12.5 mg per week for a median time of 20 months. Ninety-three percent of patients responded to MTX. One patient relapsed during treatment and was later diagnosed with lung cancer. Another 1 had a recurrence of disease 58 months after MTX discontinuation. During MTX treatment, some of the study participants were also taking low doses of GCs. It is worth noting that all of the patients in the studies describing MTX efficacy mentioned above had normal kidney function, which is not common in RPF patients. Methotrexate is contraindicated in renal insufficiency, and as a result it can only be used in a specific patient group. Notably, in the articles mentioned above, patients were treated with low doses of MTX as compared to doses of MTX administered in other autoimmune diseases.
Sirolimus
Sirolimus works by inhibiting the mechanistic target of rapamycin pathway (mTOR), which is involved in cell proliferation. Gao et al. [29] found that mTOR is activated in RPF tissues.
Eight patients with idiopathic RPF were treated with a combination therapy consisting of prednisone acetate at an initial dose of 0.8 mg/kg/day until the average time of 30.8 weeks and SRL 2 mg daily for 3 days, followed by a dose of 1 mg/day for 48 weeks.
Their fibrous masses shrank on average by almost 50%. Alleviation of symptoms, reduction of acute phase reactants levels, and improvement in kidney serum marker levels were observed during the treatment. Most of the side effects, including hyperlipidemia and hyperglycemia, among others, resolved after GC discontinuation. One patient developed shingles.
Rituximab
In a retrospective study by Oztas et al. [30], almost all of the participants were refractory to previous treatment with GCs and disease-modifying antirheumatic drugs. Intravenous infusions of 1 g of RTX were administered 1 to 6 times at 15-day intervals. In the follow-up, a relevant periaortic infiltrate regression was seen. Two out of 8 patients had ureteric stents removed. Importantly, therapy with RTX enabled prednisone discontinuation in 4 patients and dose reduction in the others. During observation, 2 patients had urinary tract infections (UTIs) that required hospitalization, but both of them had ureteric stents and UTIs in the past.
Boyeva et al. [31] presented similar results after RTX therapy. Statistically significant mass regression was noted. Two out of 10 patients had infusion-related reactions. In this study, ureteral obstruction and hydronephrosis resolution were not observed. In neither paper did the authors refer to potential disease relapses.
Tocilizumab
Wang et al. [32] confirmed the effectiveness of TCZ monotherapy in 12 patients with CP. Exclusion criteria were: secondary forms of CP, diagnosed IgG4-RD, and aneurysmal dilation. The treatment consisted of 8 mg/kg of TCZ infusions every 4 weeks for at least 3 months. In 90.9% of patients, remission was observed. The periaortic mass decreased by 70% or more in 7 study participants. In the group with initially normal serum IL-6 levels, a greater reduction of the mass was noted. The only side effect of TCZ therapy was a temporary elevation of serum liver enzymes in 2 patients.
Discussion
According to the literature, there is a broad spectrum of therapeutic alternatives in IRF, and official treatment guidelines have not yet been proposed. This review focused on the pharmacological treatment.
Although individual cases of spontaneous remission of RPF have been reported, it is considered uncommon, and treatment is usually necessary [19, 33].
Glucocorticosteroids are the cornerstone of treatment, as their effectiveness in achieving remission is reported at a rate of 70.5–91% [11–13, 27]. However, the relapse rate after GC monotherapy estimated at 17–72% remains a concern and encourages the search for other long-term therapeutic options [10–13, 26–28]. Clinical improvement occurs quickly, as symptoms typically resolve in most patients after a few weeks of GC treatment [27]. It is important to stress that there is no standardized starting dose, rate of dose reduction, or duration of treatment. In the aforementioned studies, the initial GC dose was usually 0.5–1 mg/kg/day of prednisone, and therapy lasted 6–48 months [10–13]. Tamoxifen remains a viable therapeutic option, especially in patients with contraindications to GCs. Its anti-angiogenic and anti-fibrotic effects may result in inhibition of fibroblast proliferation, although its precise mechanism of action remains unknown [34, 35]. Studies comparing the efficacy of prednisone and TMX have demonstrated the superiority of GCs in achieving remission [27]. However, results regarding the relapse rate were varied [26–28]. The most common side effects of TMX are hot flashes, fatigue, and loss of libido. Those occur in up to 51% of patients [25]. Glucocorticosteroids cause hypercholesterolemia and weight gain more frequently than TMX [26].
Both GCs and TMX may induce thromboembolic events, and GCs increase the risk of cardiovascular incidents [36–38].
Importantly, GCs may obscure the presence of a possible tumor, when the diagnosis of idiopathic RPF is ambiguous [10]. To reduce the dose and duration of prednisone therapy, adding an immunosuppressive GC-sparing drug is a meaningful solution. A wide range of options, including MTX, MMF, AZA, and CYC, allows the treatment to be adjusted to the patients’ comorbidities. Methotrexate may only be used in patients with preserved kidney function. Its effectiveness of 79–95% and low relapse rate of 14–36% have been proven in relapsing and GC-resistant patients. In a few study participants, it caused liver toxicity, and 1 patient developed sepsis [20, 21]. Taking AZA enabled ureteral stents to be removed in all treated patients, and only 7.7–26.7% of study participants had a relapse. Cyclophosphamide was also effective, although it caused serious side effects including leukopenia and sepsis, and 1 patient died of pneumonia during treatment [18, 19].
In addition to the immunosuppressive effect of MMF, it also exerts antifibrotic activity [39, 40]. Therapy with MMF resulted in 100% success according to 3 studies, reduction of periaortic mass in 86–100% of cases, and a low relapse rate of 0–23% of patients. No serious adverse effects were reported [14–17]. Recent studies have explored treatment capabilities of biological drugs in RPF. The efficacy of RTX has been proven both in idiopathic and IgG4-related RPF. Despite significant fibrotic mass regression in IRF, RTX did not resolve ureteral obstruction in many patients. Two mild reactions to infusion have been described [30, 31]. Tocilizumab and SRL are treatment alternatives worth considering, especially because their effectiveness has been proven. However, more studies are needed to properly assess their clinical relevance [29, 32].
At every stage of treatment, urological procedures should be considered. Ureteral stents and nephrostomy are preferable and have similar complication rates, while ureterolysis is a more invasive, final form of therapy, to be used when other methods have failed [41, 42].
There remain uncertainties regarding the selection of immunosuppressive therapy in patients with RPF complicated by uropathy. These patients often require more intensive treatment, yet they are at increased risk of recurrent UTIs. Cyclophosphamide and biological agents such as RTX may be effective, but their use is associated with a higher risk of all infectious complications. Among 27 patients with RPF, most of whom had IgG4-related RPF, treated with RTX by Wallwork et al. [43], 3 experienced serious infections, including UTIs, pneumonia, and herpes zoster. In a study by Marcolongo et al. [18], 1 patient treated with CYC died from pneumonia.
The definition of successful treatment in RPF remains an unresolved issue. It is paramount that the most important goal is to preserve kidney function. Therefore, resolution of ureteral obstruction and fibrous tissue shrinkage are considered important therapy success indicators [11, 17, 19, 20, 24, 27]. In some studies, the presence of only 1 of those factors was described as effective disease management [16, 18, 21, 32]. C-reactive protein and ESR normalization were considered a part of achieving remission in some studies. Acute phase reactant serum levels before treatment are suboptimal predictors of response to therapy in patients treated with GCs. High levels of CRP and ESR correlate with more severe clinical symptoms [44, 45].
Fluorodeoxyglucose positron emission tomography is a promising tool in predicting treatment response in RPF patients and disease monitoring. Patients with initially negative FDG uptake are less likely to respond to therapy compared to patients with positive FDG-PET [46–48]. It is worth noting that in most individuals who achieved remission, periaortic tissue remains present. However, it is not usually metabolically active and does not indicate the possibility of recurrence [49]. Importantly, detection of antinuclear antibodies, female sex, higher prednisone dosage in the first year of treatment, and initial monotherapy with GCs or therapy with GCs and TMX compared with other drugs are associated with lower relapse rates [50].
Conclusions
There are multiple difficulties in determining the appropriate treatment regimen of IRF. First of all, due to the rarity of the disease, studies are conducted on small groups of patients, and the majority of them are retrospective. Numerous medications have been demonstrated to be effective, but so far no standardized clinical practice guidelines have been developed. Another important issue is the high relapse rate, necessitating long-term follow-up for most patients. Creating treatment recommendations requires more studies with larger patient groups and more randomized controlled trials.


